Adult female acne 2026: hormonal subtype and what works
Why adult-onset acne in women is often hormonally driven, how it differs from adolescent acne, and what the evidence supports for combined oral contraceptives, spironolactone, and topical therapy.
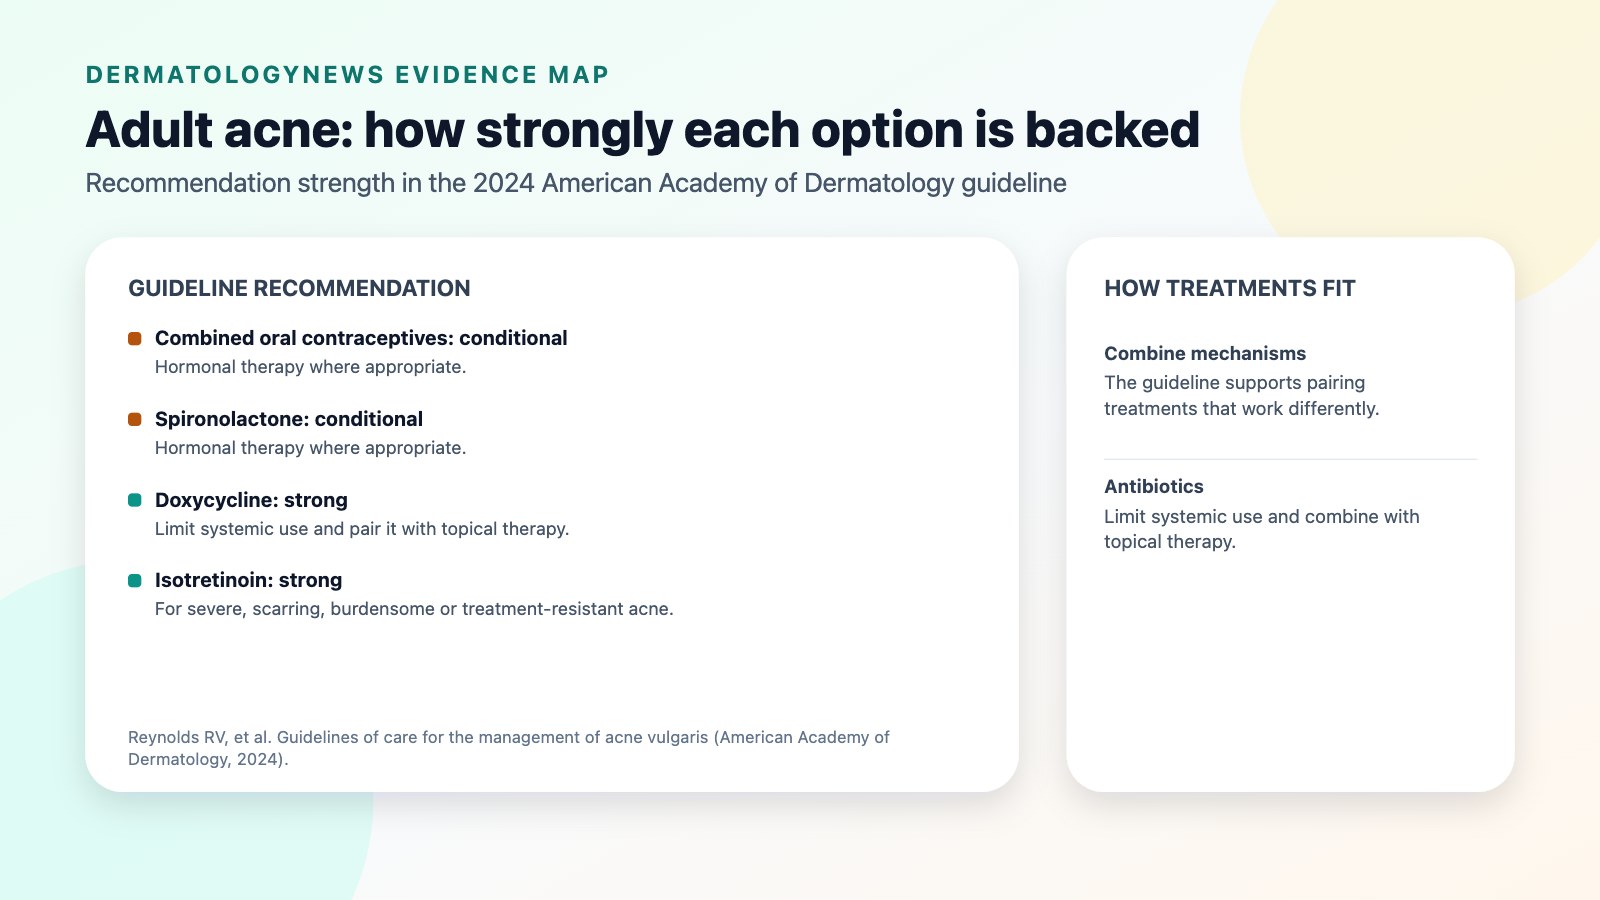
Adult female acne is a clinically distinct entity from adolescent acne, and the management approach increasingly reflects that. Where teenage acne is often centered on the T-zone and dominated by comedonal disease, adult-onset and persistent acne in women is more often inflammatory, more often jawline-distributed, more often hormonally responsive, and more often associated with anxiety and depression [2]. The 2024 AAD guideline supports topical therapy and conditionally recommends combined oral contraceptives and spironolactone when appropriate [1].
Clinical pattern
The 2019 Anais Brasileiros de Dermatologia practice guide articulates the distinguishing features of adult female acne [2]:
- Onset: persistent from adolescence (continuous) or appearing for the first time in adulthood (late-onset).
- Distribution: lower third of the face, jawline, perioral, and chin more than the forehead and central T-zone.
- Lesion type: inflammatory papules and nodules predominate; comedones may be less prominent than in adolescents.
- Pattern: premenstrual flare in many patients; flares correlated with stress, oral contraceptive changes, and certain medications.
- Psychological impact: significantly associated with anxiety and depression — sometimes more so than the visible severity would predict.
Patients often describe a frustrating pattern of trying multiple over-the-counter cleansers and topical products without sustained improvement. The clinical pivot is recognizing that the driver may be hormonal, not topical bacterial.
When to evaluate for underlying conditions
The 2019 practice guide and 2020 international PCOS guideline together inform when laboratory or specialist workup is appropriate [2][3]:
- Hirsutism (terminal hair growth in male-pattern distribution).
- Irregular menstrual cycles by adult criteria (cycles shorter than 21 days or longer than 35 days more than 3 years post-menarche, or primary amenorrhea).
- Rapid weight gain or central obesity.
- Sudden severe acne with virilization signs.
- Hair thinning in a male-pattern distribution.
Hyperandrogenic signs or menstrual irregularity can warrant assessment for polycystic ovary syndrome (PCOS) or another endocrine condition [2][3]. Rapid-onset virilization requires prompt evaluation for causes beyond PCOS. Tests such as testosterone and dehydroepiandrosterone sulfate (DHEAS), and imaging when indicated, depend on the clinical findings; adolescent assessment requires age-appropriate criteria [3].
Routine hormonal panels are not recommended for every patient with adult female acne — only when clinical features warrant it.
Treatment categories
The 2024 AAD acne guideline supports combining treatments with different mechanisms, limiting systemic antibiotic use, and pairing antibiotics with topical therapy [1]. Combined oral contraceptives and spironolactone receive conditional recommendations [1].
Topical therapy
The foundation of treatment for most patients:
- Retinoids (tretinoin, adapalene, tazarotene): normalize follicular keratinization, reduce comedones, and have anti-inflammatory effects. First-line topical agent.
- Benzoyl peroxide: bactericidal against Cutibacterium acnes with no documented resistance; combination with topical antibiotics is standard.
- Topical antibiotics (clindamycin, erythromycin): always combined with benzoyl peroxide to prevent resistance.
- Azelaic acid: anti-inflammatory and tyrosinase-inhibiting; particularly useful for patients with concurrent post-inflammatory hyperpigmentation.
- Clascoterone and salicylic acid: additional topical options with conditional recommendations in the 2024 guideline [1].
Systemic antibiotics
- Doxycycline has a strong recommendation; minocycline and sarecycline have conditional recommendations [1]. Limit systemic antibiotic use and combine it with benzoyl peroxide and other topical therapy.
Hormonal therapy: a distinguishing feature of adult female acne
- Combined oral contraceptives (CHC): four CHCs are FDA-approved for acne. They reduce androgen effects on sebaceous glands. Contraindications include thromboembolism history, migraine with aura, smoking over age 35, and certain other conditions.
- Spironolactone: an aldosterone antagonist with anti-androgen effects. Off-label but widely used in dermatologic practice with a favorable safety profile in healthy young women. Recent dermatologic guidance has reduced or eliminated routine potassium monitoring for healthy patients. Effective doses range from 50 mg to 200 mg daily.
Combination of topical retinoid + benzoyl peroxide + spironolactone is a common contemporary regimen for inflammatory adult female acne [2].
Isotretinoin
- Strongly recommended for severe acne, acne causing psychosocial burden or scarring, or acne that fails standard oral or topical therapy [1]. iPLEDGE program participation is required in the United States. Pregnancy is a strict contraindication during and for one month after treatment. Effective monitoring is essential.
Procedural and adjunctive options
- Chemical peels and laser/light procedures: the 2024 AAD guideline found insufficient evidence to make treatment recommendations [1].
- Microneedling and fractional lasers: for acne scars after active disease is controlled, not for active inflammatory acne.
Common pitfalls
- Topical-only approaches for moderate or hormonally driven acne: often insufficient. The pivot to systemic or hormonal therapy is appropriate when topicals plateau.
- Over-cleansing and aggressive exfoliation: increases irritation and post-inflammatory pigmentation, particularly in Fitzpatrick III–VI skin.
- Long-term oral antibiotic monotherapy: drives C. acnes resistance. Combination with benzoyl peroxide and time-limited courses are the standard.
- Stopping treatment when skin clears: relapse is common; maintenance with a topical retinoid is the conventional plan.
- Untreated psychological impact: anxiety and depression screening and referral are part of comprehensive care.
Patient counseling expectations
- Most regimens require 8 to 12 weeks to demonstrate meaningful improvement.
- Initial worsening (purge) is possible with topical retinoids in the first 4 to 6 weeks.
- Maintenance therapy is usually needed for years, not weeks.
- Sun protection helps limit post-inflammatory pigmentation after acne.
Evidence for hypochlorous acid face sprays remains specific to the products and clinical settings studied.
Bottom line
Adult female acne is most often inflammatory, hormonally responsive, and persistent — and management should reflect that [1][2]. A multimodal regimen combining topical therapy with selectively added hormonal agents (combined oral contraceptives or spironolactone) is the contemporary standard. Evaluation for underlying PCOS or other hormonal conditions is appropriate when clinical features warrant it [3]. Treatment is usually long-term, and adjunct psychological support is part of comprehensive care.
Common questions
- How is adult female acne different from teenage acne?
- Adult female acne tends to involve the lower face, jawline, and chin more than the T-zone, and is more often hormonally driven. It is also more likely to persist or recur over years, and is more strongly associated with anxiety and depression than adolescent acne.
- Do I need hormone testing?
- Laboratory testing is typically considered when acne is accompanied by other signs of hyperandrogenism such as hirsutism, irregular menstrual cycles, or rapid weight changes. Most adult female acne does not require routine hormone panels unless these features are present.
- Is spironolactone safe for long-term use?
- Spironolactone is used off-label for adult female acne with a generally favorable long-term safety profile in dermatologic practice. Common side effects include menstrual irregularity, breast tenderness, and dehydration; routine potassium monitoring is no longer required in healthy young women per recent dermatologic guidance.
- Can birth control pills help acne?
- Combined oral contraceptives (containing both estrogen and progestin) are FDA-approved for certain acne indications. They are commonly considered as part of a multimodal plan, particularly when contraception is also desired. Risks include thromboembolism and require individualized assessment.
- Will my acne clear during pregnancy?
- Pregnancy can either improve or worsen acne, and it is unpredictable. Treatment during pregnancy is limited because retinoids, spironolactone, and tetracyclines are contraindicated. Topical azelaic acid and certain benzoyl peroxide formulations are commonly considered acceptable; consult an OB-GYN and a dermatologist.
References
- Reynolds RV et al. Guidelines of care for the management of acne vulgaris. — Journal of the American Academy of Dermatology, 2024 · PMID: 38300170 · DOI: 10.1016/j.jaad.2023.12.017
- Bagatin E et al. Adult female acne: a guide to clinical practice. — Anais Brasileiros de Dermatologia, 2019 · PMID: 30726466 · DOI: 10.1590/abd1806-4841.20198203
- Peña AS et al. Adolescent polycystic ovary syndrome according to the international evidence-based guideline. — BMC Medicine, 2020 · PMID: 32204714 · DOI: 10.1186/s12916-020-01516-x
- American Academy of Dermatology — Acne: Diagnosis and Treatment patient resource. — American Academy of Dermatology